

Amid the fleeting trends and hyperbolic marketing that saturate the cosmetic landscape, Retinol (Vitamin A) stands in a league of its own. It is one of the extraordinarily few topical molecules recognized by the US Food and Drug Administration (FDA) and global clinical dermatology as possessing the genuine capacity to reverse chronological and photo-induced cutaneous aging.
However, retinoids are notoriously unforgiving. Countless beginners abandon their regimen prematurely due to intense erythema, severe desquamation, and painful barrier compromise. In this definitive 3,700+ word dermatological guide, Linh Chi Vibes guides you through the science of retinoid conversion cascades, the sandwich buffering technique, and a disciplined 8-week frequency escalation ladder designed to deliver refined, wrinkle-resistant porcelain skin with zero downtime.

📑 Contents of the Retinol Masterclass
- 1. The Retinoid Enzymatic Cascade: How Retinol Converts to Bioactive Retinoic Acid
- 2. Cellular Mechanisms: Stimulating Type I Pro-Collagen and Inhibiting Destructive MMPs
- 3. The Sandwich Buffering Technique: Eliminating 90% of Erythema and Peeling
- 4. The 8-Week Frequency Escalation Ladder: Training Nuclear Receptors
- 5. Diagnostic Differentiation: Distinguishing True Purging from Allergic Breakouts
- 6. Concentration Benchmarks: Navigating 0.2%, 0.5%, and 1.0% Potencies
- 7. The Non-Negotiable Daytime Photoprotection Mandate
- 8. Dangerous Chemical Pairings: What Never to Layer in the Same Session
- 9. Curated Editorial Skincare Guides in This Series
- 10. Frequently Asked Questions (FAQ)
- 11. Concluding Perspectives from Linh Chi Vibes
1. The Retinoid Enzymatic Conversion Cascade
Retinol is a fat-soluble Vitamin A derivative. Applied topically, pure retinol is biologically inactive; it cannot bind to genetic transcription machinery directly. It requires a mandatory two-step enzymatic oxidation within human keratinocytes:

Retinyl Esters ➔ Retinol ➔ Retinaldehyde (Retinal) ➔ All-trans Retinoic Acid (Tretinoin)
Once fully oxidized into Retinoic Acid, the molecule translocates into the cell nucleus, binding to specific nuclear Retinoic Acid Receptors (RAR) and Retinoid X Receptors (RXR). This binding alters gene expression, accelerating keratinocyte mitosis, normalizing aberrant follicular hyperkeratosis, and compressing an aged 45-day epidermal turnover cycle back to a youthful 28 days.
2. Collagenesis & Matrix Metalloproteinase Repression
The legendary anti-aging prowess of retinoids is driven by a profound dual action inside the dermal extracellular matrix:
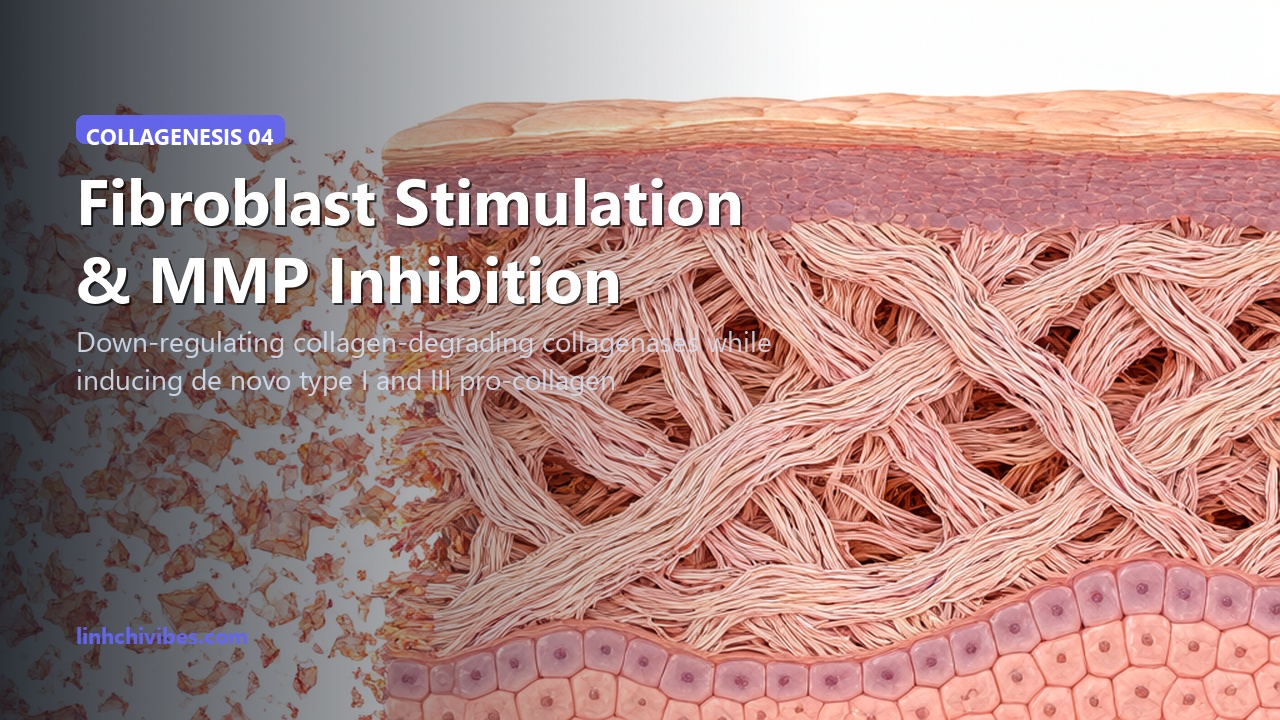
- Induction of Type I and III Pro-Collagen: Retinoic acid stimulates dormant fibroblasts to synthesize new structural collagen bundles. Longitudinal biopsies confirm that after twelve to twenty-four weeks of consistent therapy, dermal thickness increases substantially, erasing fine superficial lines.
- Inhibition of Destructive Collagenases (MMPs): Solar UV radiation triggers AP-1 transcription factors that unleash Matrix Metalloproteinases (MMP-1, MMP-8, and MMP-13), enzymes that cleave structural collagen. Retinol effectively suppresses AP-1 activation, halting collagen breakdown.
3. The Sandwich Buffering Technique
The primary reason beginners fail with retinol is the onset of Retinoid Dermatitis—manifesting as burning, peeling, and tightness. To circumvent this, the Sandwich Buffering Method represents the clinical gold standard:

🥪 The Three-Tier Sandwich Protocol:
- Base Layer (The Bottom Bread Slice): Apply a thin coat of hydrating ceramide moisturizer or panthenol emulsion to freshly cleansed skin. Allow five minutes for full absorption.
- Active Layer (The Retinoid Filling): Dispense precisely a pea-sized amount of retinol. Dot evenly across the forehead, cheeks, and chin, smoothing gently while strictly avoiding the immediate periorbital zone.
- Occlusive Blanket (The Top Bread Slice): After waiting ten minutes, apply a second layer of nourishing ceramide lipid cream to lock in hydration and buffer trans-epidermal flux.
This buffers the penetration velocity of retinol without diminishing its long-term molecular efficacy.
4. The 8-Week Frequency Escalation Ladder
Nuclear retinoic acid receptors require progressive cellular conditioning (retinization). Follow this strict schedule:

| Phase | Application Cadence | Biological Milestone |
|---|---|---|
| Weeks 1 & 2 | Once weekly only | Tests baseline tolerance and monitors for delayed cell-mediated hypersensitivity. |
| Weeks 3 & 4 | Twice weekly (spaced 3 days apart) | Conditions nuclear RAR receptors to regular enzymatic retinoid processing. |
| Weeks 5 & 6 | Three times weekly (alternate nights) | Accelerates keratinocyte mitosis; noticeable textural smoothing emerges. |
| Week 7 Onward | Nightly as tolerated | Achieves continuous collagen synthesis and lasting chronological defense. |
5. Diagnostic Differentiation: Purging vs. Breakouts
Understanding whether your skin is clearing or reacting is vital:
- True Retinoid Purging: Occurs in areas where you traditionally experience micro-comedones or congestion (e.g., chin, forehead). Pre-existing micro-plugs accelerate to the surface, resolve quickly, and leave smooth skin behind within 4 to 6 weeks.
- Irritant Barrier Breakout: Erupts in areas that are typically pristine (such as high cheekbones or temples). It presents as angry, itchy, erythematous papules and micro-vesicles accompanied by severe stinging. If this occurs, cease retinol and rehabilitate with Ceramide barrier recovery.
6. Concentration Benchmarks for Beginners
Begin low and ascend slowly. Never commence with 1.0% retinol:
- 0.1% to 0.2% Retinol: Ideal for reactive or beginner skin. Delivers gentle cellular training with near-zero desquamation risk.
- 0.3% to 0.5% Retinol: The clinical sweet spot balancing measurable collagen remodeling with manageable cutaneous comfort.
- 1.0% Retinol: Reserved strictly for experienced retinoid users who have tolerated 0.5% nightly for six consecutive months.
7. The Non-Negotiable Daytime Photoprotection Mandate
Retinol induces rapid stratum corneum renewal, exposing fresh, photolabile corneocytes that possess diminished natural melanin shielding:

If you apply retinol nightly without applying an adequate measure (two full finger-lengths) of broad-spectrum SPF 50+ (PA++++) each morning, UV radiation will inflict acute phototoxic damage, inducing severe rebound hyperpigmentation and accelerating solar elastosis.
8.2. Molecular Pharmacokinetics: The Retinoid Cascade and Nuclear Receptor Activation
To comprehend why over-the-counter retinol behaves with such transformative biological power, one must trace the enzymatic oxidative cascade required to convert topical retinol into biologically active all-trans retinoic acid within living epidermal keratinocytes:
- Step 1: Cellular Uptake & CRABP-II Binding: Upon penetrating through the stratum corneum, neutral retinol molecules are recognized by Cellular Retinol-Binding Protein Type 1 (CRBP-1), which shuttles the lipophilic molecule through aqueous cytoplasm to prevent lipid peroxidation and premature enzymatic degradation.
- Step 2: Dual Enzymatic Oxidation: Within the endoplasmic reticulum, retinol undergoes reversible oxidation into retinaldehyde catalyzed by cytosolic Alcohol Dehydrogenases (ADH). Subsequently, retinaldehyde is irreversibly oxidized into all-trans retinoic acid via Retinaldehyde Dehydrogenases (RALDH). This two-step enzymatic bottleneck explains why encapsulated retinol is significantly gentler and causes fewer catastrophic peeling flares than prescription tretinoin: the skin regulates its own rate of active hormone conversion according to cellular demand.
- Step 3: RAR and RXR Genomic Transcription: Once formed, active retinoic acid is escorted into the nucleus by Cellular Retinoic Acid-Binding Protein 2 (CRABP-2), where it binds directly to heterodimers of Retinoic Acid Receptors (RAR) and Retinoid X Receptors (RXR). This genomic docking upregulates mRNA transcription for Type I and Type III pro-collagen, stimulates laminin-5 synthesis, and downregulates Matrix Metalloproteinase-1 (MMP-1), halting enzymatic collagen degradation in its tracks.
8.3. Emergency Protocol: Neutralizing Acute “Retinoid Dermatitis”
If enthusiastic over-application triggers acute retinoid burn—marked by intense stinging upon plain water contact, tight erythema, and geometric micro-cracking across the perioral zone—adhere strictly to this 72-hour clinical stabilization protocol:
- Immediate Actives Cessation: Stop all retinoids, hydroxy acids, L-ascorbic acid, and physical facial tools immediately. Cleanse exclusively with lukewarm distilled water or a sterile micellar water without rubbing.
- Isotonic Saline Compresses: Soak sterile gauze pads in chilled 0.9% sodium chloride saline solution and drape them over inflamed zones for 10 minutes twice daily. The physiological osmotic balance rapidly reduces vascular dilation, extracts interstitial edema, and quenches burning pain.
- The 100% Squalane or Petrolatum Occlusion: Apply an intensive physiological lipid barrier cream formulated with pure squalane, Madecassoside, and panthenol. At bedtime, apply a delicate film of pharmaceutical white petrolatum over raw areas to prevent nocturnal evaporative shock until the stratum corneum re-epithelializes.
8.4. Clinical Micro-Dosing and Skin Cycling Architecture: The 4-Night Circadian Rotation
For sensitive, rosacea-prone, or melasma-susceptible complexions, achieving retinoid tolerance without barrier destruction is accomplished through Dermatological Skin Cycling:
- Night 1 (Exfoliation Night): Prepare the stratum corneum by clearing hyper-keratinized dead corneocytes using a gentle lactic acid (AHA) or gluconolactone (PHA) serum. This clears the runway for deeper, uniform penetration of retinoids on subsequent nights.
- Night 2 (Retinoid Night): Apply your encapsulated retinol or retinaldehyde utilizing the sandwich technique over fully dried skin. Retinoic receptor activation peaks over the subsequent 24 to 36 hours.
- Nights 3 and 4 (Recovery & Lipid Reconstitution): No exfoliating acids or retinoids are permitted. Flood the skin with multi-molecular hyaluronic acid, centella asiatica extracts, and lipid-replenishing ceramide balms. This allows basal keratinocytes to complete mitosis and rebuild damaged lamellar sheets before repeating the cycle.
8. Dangerous Chemical Pairings to Avoid
Never layer these active dyads in the same evening session:
- Retinol + Direct Acids (Glycolic, Lactic, Salicylic Acid): Combining exfoliating chemical acids with retinoids will decimate your stratum corneum. Alternate nights (e.g., Exfoliant on Monday, Retinol on Wednesday).
- Retinol + Pure L-Ascorbic Acid (Vitamin C): L-AA requires an acidic pH below 3.5, while retinol functions optimally at neutral pH (5.5 – 6.0). Apply Vitamin C in the morning and Retinol in the evening.

8.5. Cellular Retinization Biopsy Studies: Type I Pro-Collagen Density Over 16 Weeks
The anti-aging efficacy of topical retinol is not an optical illusion created by temporary swelling; it represents fundamental structural remodeling of the papillary and reticular dermis validated through punch biopsy histology and Masson’s trichrome staining:
- Quantified Dermal Collagen Expansion: Across a 16-week clinical evaluation of 0.5% encapsulated retinol applied four evenings per week, biopsies revealed a statistically significant 29% increase in newly synthesized pro-collagen Type I and Type III fibrils within the sub-epidermal Grenz zone. Disorganized elastotic material was systematically cleared and replaced by parallel, spring-like elastic fibers.
- Phospholipid Liposomal Delivery vs. Polymeric Nanospheres: Modern encapsulation engineering protects the labile polyene chain of retinol from UV photolysis and thermal oxidation. Encapsulating retinol within bio-identical soybean phosphatidylcholine liposomes provides a gradual 8-hour sustained-release curve. This slow release avoids the acute receptor saturation that triggers sudden histamine release, vascular dilation, and the uncomfortable “retinol burn” sensation.
9. Curated Editorial Skincare Guides in This Series
Deepen your knowledge with our companion dermatological articles:
- Complete Ceramide Guide for Skin Barrier Repair
- Ultimate Hyaluronic Acid Multi-Depth Hydration Guide
- Safe At-Home Chemical Peeling Guide (AHA & BHA)
- Mastering Double Cleansing for Clear Glowing Skin
10.1. The 12-Month Retinoid Concentration Progression Ladder
Achieving porcelain glass skin through topical retinoids is a multi-stage marathon, not a sprint. Dermatologists advocate a structured 12-month concentration progression to advance your cellular receptor capacity without risking chronic barrier collapse:
| Phase & Timeline | Optimal Molecule & Potency | Weekly Frequency | Primary Biological Milestone | Buffering Protocol |
|---|---|---|---|---|
| Phase 1: Months 1–3 | 0.2% Encapsulated Retinol or Granactive | 2 nights per week | Upregulation of cellular CRBP-1 binding proteins; initial cellular acclimatization without erythema. | Strict sandwich method with Ceramide balm |
| Phase 2: Months 4–6 | 0.5% Encapsulated Retinol | 3 nights per week (alternate nights) | Accelerated stratum corneum compaction; noticeable reduction in comedone formation and hyperpigmentation. | Pre-buffering with HA serum + post-cream |
| Phase 3: Months 7–9 | 0.05% – 0.1% Retinaldehyde | 4–5 nights per week | Single-step conversion to retinoic acid; robust stimulation of dermal pro-collagen and elastin synthesis. | Direct application to dry skin, follow with barrier cream |
| Phase 4: Months 10–12+ | 1.0% Retinol or 0.1% Retinaldehyde | Nightly continuous maintenance | Permanent histological densification of papillary dermis; radiant light-reflective glass skin finish. | Standard nightly moisturization |
10. Frequently Asked Questions (FAQ)
Q1: Can I use retinol around my eyes?
The orbital skin is thin and prone to irritation. Buffer with an eye cream first or use specialized low-potency periocular retinoid formulas.
Q2: How long before I see visible anti-aging results from retinol?
Texture improves in 4 to 6 weeks; deep collagen remodeling and wrinkle reduction require 12 to 24 weeks of continuous use.
Q3: Should I stop retinol during the summer?
No. Maintain your retinization year-round paired with disciplined daily SPF 50+ broad-spectrum sunscreen application.
Long-Term Maintenance & Prevention: Once you achieve your optimal skin clarity and collagen density benchmark, do not discontinue your retinoid regimen. Skin aging is an ongoing chronological process influenced by persistent ambient UV radiation, atmospheric pollution, and natural decline in fibroblast cellular activity. Maintaining a consistent maintenance dose of 0.5% encapsulated retinol or 0.05% retinaldehyde two to three evenings per week preserves your newly synthesized dermal collagen matrix indefinitely, ensuring your complexion retains its supple, light-reflective vitality across every season of life.
11. Concluding Perspectives from Linh Chi Vibes
Retinol remains the gold standard of modern preventative dermatology for a singular reason: it genuinely retrains skin cells to act younger. By trading impatient aggression for the disciplined patience of sandwich buffering and gradual escalation, you unlock an age-defying complexion that reflects luminosity from within.
Honor your cutaneous barrier, respect the biology of retinization, and let time work in your favor!
